Yes, scrolling can make you dizzy: your eyes report motion while your inner ear and body report stillness, and that mismatch is thought to set off the symptoms in some people.
Dizziness when scrolling is what happens when the picture in front of your eyes moves and the rest of your balance system reports that nothing is moving at all. It says nothing about fragility, and nothing is wrong with the phone. Most people’s brains shrug that off. Some brains do not, and if yours is one of them, you may already have been told it is eye strain, anxiety, or too much time online.
I am Dr. Alireza Chizari, DC, DACNB, a Board-Certified Functional Neurologist, and at California Brain & Spine Center in Calabasas the screen question comes up in almost every dizziness evaluation now, whether or not it was the reason for the visit. People describe the feed that makes them queasy on the 101, the spreadsheet that leaves them swaying at four in the afternoon, the video call after which the room keeps drifting. The pattern is real, it is common, and it is worth understanding properly, because the same symptom has a few very different causes and the fixes are not the same.
Key Takeaway
Scrolling makes some people dizzy because the eyes report motion while the inner ear and body report stillness, and the brain is thought to treat that conflict as movement. Device settings and habits can reduce it today. When it is frequent, lasts beyond the screen, or comes with migraine, a head injury or a balance problem, it deserves a proper evaluation.
Why Does Scrolling on My Phone Make Me Dizzy?
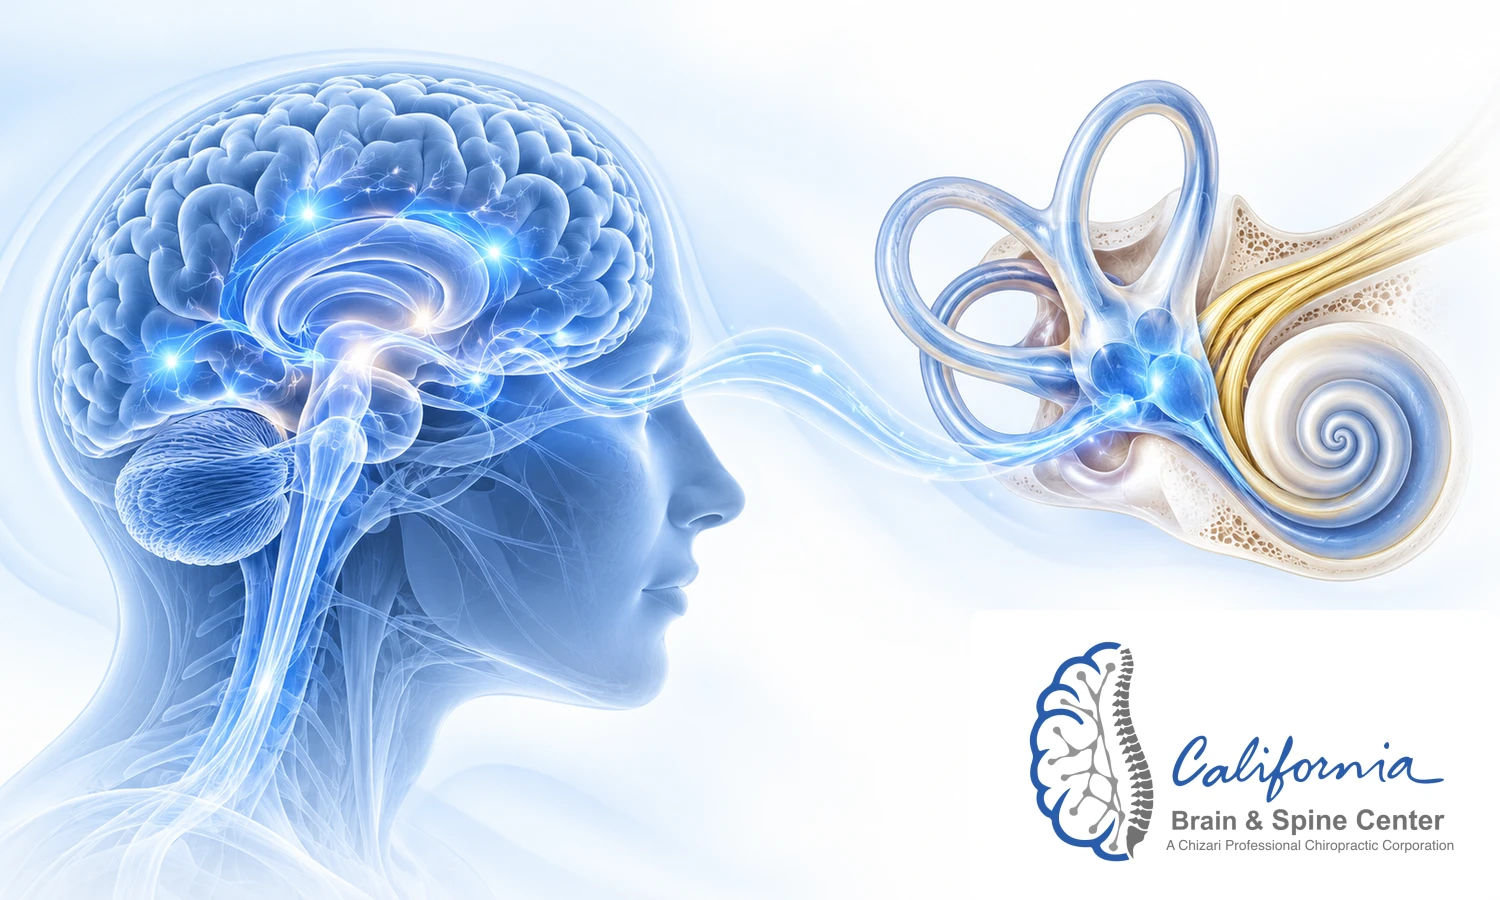
Your brain works out whether you are moving by combining reports from the inner ears, the eyes, and the muscles and joints. MedlinePlus, the National Library of Medicine’s patient resource, puts the rule in one sentence: when the brain gets signals that do not match, you can get motion sickness. Its own example is reading on a phone while riding a bus, where the eyes are fixed on something still while the inner ear senses motion. Scrolling is that example turned inside out. Now the eyes report a world sliding past while the inner ear and the body report a person sitting perfectly still, and the mismatch is the same.
The sensation that follows dizziness when scrolling has a range. For some people it is a faint sway that passes when they look up. For others it is the full motion-sickness sequence, which MedlinePlus describes as a queasy feeling and cold sweats that can lead to dizziness, nausea and vomiting. Where you land on that range depends less on the phone than on how your balance system is weighted, and that weighting is what a dizziness evaluation in Calabasas is designed to look at.
Why some people feel it and most do not
The Vestibular Disorders Association describes two explanations that clinicians use, and they are not competing. Most researchers believe visually induced dizziness comes from a mismatch between the parts of the brain’s balance system, the same conflict as motion sickness. Others believe it happens when a vestibular problem, meaning a fault in the inner-ear balance system, has taught the brain to rely too heavily on visual signals, a habit called visual dependency, so that when vision and the other senses disagree, the brain sides with the eyes and decides you are moving when you are not. People with a vestibular disorder rely heavily on the visual system to stay upright, and a screen’s lights, motion, print and colours can all challenge a brain that is already sensitive. That is why a person with a mild inner-ear problem from years ago can be fine walking down the street and undone by a feed, and why visual motion sensitivity so often shows up first in a supermarket aisle or a scrolling thumb before it shows up anywhere a clinician would think to look.
Why scrolling makes some people nauseous rather than dizzy
Nausea and dizziness sit on the same symptom list for these episodes. The Vestibular Disorders Association’s list of what an episode of visually induced dizziness may bring runs from dizziness and unsteadiness through light-headedness, disorientation, nausea, vomiting, sweating, a watering mouth, tiredness and turning pale, and some people say it feels like seasickness or being drunk. If scrolling makes you nauseous, you are describing the gut end of that list. If it makes you feel you might fall, you are describing the balance end. The trigger is the same moving picture.
What Is Digital Vertigo?
Digital vertigo is the everyday name for dizziness, unsteadiness or nausea set off by a screen: scrolling, a video, a busy video call, a fast game. It is a description rather than a diagnosis. Clinicians call the same thing visually induced dizziness or visual vertigo, and the useful question is which balance system the moving picture is provoking.
The clinical umbrella is wide on purpose. The Vestibular Disorders Association uses visually induced dizziness as the umbrella term for a group of symptoms that come from some vestibular disorders, and notes it is also called visual vertigo, space and motion discomfort, supermarket syndrome or visual vestibular mismatch. None of those labels tells you why your brain is doing it. A migraine brain, a post-concussion brain, a brain compensating for an old inner-ear problem and a brain that has simply become visually dependent can all produce digital vertigo, and they are not treated the same way.
What digital vertigo feels like from the inside
The descriptions I hear are remarkably consistent. A slow drift of the room after the phone is put down. A wave of warmth and a queasy stomach a few minutes into a feed. The sense, on a video call with several moving faces, that the floor has become slightly unreliable. Some people notice tiredness out of proportion to what they did. Most notice that looking up and out at something still settles it, which is exactly what MedlinePlus recommends for motion sickness in a vehicle: looking out into the distance instead of at something close.
Why it is a description and not a diagnosis
Persistent postural-perceptual dizziness, usually shortened to PPPD, is a chronic form of visually provoked dizziness. In the Bárány Society’s diagnostic criteria, its symptoms are exacerbated by upright posture, active or passive movement, and exposure to moving or complex visual stimuli. The diagnosis rests on the history and on those published criteria. A screen is a visually complex environment you carry in your pocket. That is why dizziness when scrolling can be the first sentence of a story that turns out to be about PPPD, and why the label “digital vertigo” on its own settles nothing.
Can Too Much Screen Time Cause Dizziness or Vertigo?
Screen time can provoke it, and the distinction between dizziness and vertigo matters here. MedlinePlus is precise: dizziness can make you feel lightheaded, woozy or unsteady on your feet, while vertigo is the feeling that you or the room is spinning even when nothing is moving. Most screen-triggered symptoms are dizziness in that sense, a sway or a queasy unsteadiness. True spinning vertigo from a screen, when it happens, is a stronger reason to have the inner ear and the migraine history looked at, because MedlinePlus lists inner ear problems, motion sickness, migraines and head injury among the common causes of both.
The honest answer to whether more screen time makes it worse is that large areas of complex patterns or movement, such as supermarket shelves, moving traffic or movies on a big screen, can make long-lasting dizziness or unsteadiness worse, and a feed is a large area of complex movement held eight inches from the face. The sources describe provocation, not damage. What the hours do is expose a system that was already weighted toward vision, over and over, until the person notices. The screen is the stress test, not the disease.
When Dizziness When Scrolling Points to Something Else
Four situations change what I recommend, and each has a signature. Migraine is the first: people with migraine may be sensitive to light, noise and smells, and may feel dizzy, per the National Institute of Neurological Disorders and Stroke. A person whose screen dizziness arrives with a headache, or with light sensitivity, or in the days around their usual migraine pattern, has a migraine question before they have a screen question.
A recent head injury is the second. The CDC lists dizziness or balance problems, vision problems and being bothered by light among the recognised symptoms of concussion, and MedlinePlus has a plain-language guide to concussion. If the scrolling problem began after a fall, a collision or a sports hit, the screen is reporting a brain that is still healing. The third is an inner-ear history, old or new, because some researchers believe that is where visual dependency begins. The fourth is PPPD, described above: dizziness on most days for months, worse upright and in visually busy places.
| What patients typically describe | Patterns that suggest something more | What the evaluation looks at |
|---|---|---|
| A queasy sway during a long scroll that settles when they look up | Dizziness that outlasts the screen by hours, or is there on most days | How long each episode lasts and whether a still world settles it |
| Worse on a moving bus or in the passenger seat | Worse in supermarket aisles, crowds and patterned floors as well | Visual motion sensitivity across settings, not only on the phone |
| Occasional, after a heavy screen day | Arrives with headache, light sensitivity or a known migraine pattern | The migraine history, including aura symptoms |
| Started gradually, no clear beginning | Started after a head injury, a fall or an ear infection | The event that preceded it and what has changed since |
| Unsteady, woozy, hard to describe | The room spins, or hearing changes with it | Inner-ear function, hearing and the gait and balance exam |
| Better with a break | Better only with avoidance, so life has quietly shrunk | Whether the pattern has become persistent and how much it is costing |
When Dizziness Is an Emergency, Not a Screen Problem
Sudden or severe dizziness or vertigo with vision problems, slurred speech or weakness is an emergency whatever you were looking at when it started.
If symptoms come on suddenly or severely – a sudden severe headache, weakness, trouble speaking, vision loss, or fainting – that is an emergency. Call 911 or go to an emergency room, not a clinic appointment.
Tired of Guessing What the Screen Is Doing?
If the settings below help but the pattern keeps coming back, the next step is a measured look at the balance system. Dizziness and vertigo care in Calabasas starts with an evaluation that tests the eyes, the inner ear and the balance response before anyone suggests a treatment.
What Helps Dizziness When Scrolling Right Now?
Start with the device, because the changes cost nothing and the Vestibular Disorders Association’s guidance on digital devices is practical. Set the brightness to closely match the room around you. Try the night or dark display settings. Under Accessibility, find Motion and switch the reduce-motion toggle on, and switch autoplay effects off. Look away from the device often, bring it to eye level rather than looking down at it, sit the appropriate distance from the screen, and limit screen time. The one-line version of all of that is the same advice MedlinePlus gives for a car: look out into the distance instead of at something close, because a still horizon gives the brain the report it needs to settle the argument.
Then look at where the scrolling happens. The feed on a moving bus is the worst possible combination, a screen in motion inside a body in motion, and moving that reading to a stationary seat later in the day removes one of the two conflicting signals. At a desk, the same principles apply to a monitor, and setting up a vertigo-friendly workspace is mostly a matter of screen height, distance, light and breaks rather than equipment.
Digital vertigo treatment: what an evaluation adds
Settings reduce the provocation. They do not change the weighting of a balance system that has learned to over-trust the eyes, which is why some people do everything on the list and still feel the feed. The Vestibular Disorders Association is clear that treatment for visually induced dizziness partly depends on what is causing it: treating an underlying condition such as migraine with dizziness may help with some symptoms, and vestibular rehabilitation can help by giving controlled exposure to the things that trigger dizziness, with the goal of retraining the balance system and reducing visual dependency.
That is the sense in which an evaluation adds something a settings menu cannot. A provider may check hearing, balance and how you walk, in MedlinePlus’s plain description, and a functional neurology evaluation goes further into how the eyes hold and track a target, how the inner ear answers movement, and how the balance response behaves with the eyes open and closed. Where the results point to visual dependency or a vestibular problem, vestibular rehabilitation is offered when clinically appropriate after that evaluation, built around the specific trigger rather than a generic programme. Where they point to migraine or a healing concussion, the plan is different, and it would be wrong to sell one plan to all four.
Many of the people who ask me about this live and work along the 101, in Calabasas, Encino and the surrounding valley, and the commute is often part of the question: the reading that happens on the freeway, the calls that happen in the car. A question I hear often is why cutting screen time in half did not change much, and that question is itself a clue that the screen may not be the whole explanation.
What Does a Dizziness Evaluation in Calabasas Look At?
A dizziness evaluation at our Calabasas clinic looks at how your eyes hold and follow a target, how your inner ear answers movement, and how your balance behaves with your eyes open and closed. It starts with the history, because the history often narrows the question before any test does: whether there was a head injury, an earlier episode of spinning, migraine in you or your family, and whether supermarkets, crowds or patterned floors have become unpleasant as well. The first visit is a 120-minute neurodiagnostic assessment, which leaves time for both the conversation and the testing, and I explain each result and what it may mean for the screen symptoms before we talk about any care.
One question patients often ask me is whether digital vertigo is a real diagnosis. It is an informal description. The clinical term is visual vertigo, which a study in the journal Brain describes as a pattern in which symptoms are provoked or aggravated by specific visual contexts. The same research suggests visual vertigo may emerge in people with a vestibular problem who rely more heavily on vision and have difficulty resolving conflict between what the eyes and the balance system report. That is why I test balance with the eyes closed as well as open: a system that leans on vision may look steady until the eyes are taken away.
When dizziness when scrolling continues after the habits have changed, I think about persistent postural-perceptual dizziness. In the Bárány Society’s diagnostic criteria, PPPD symptoms are exacerbated by upright posture, active or passive movement, and exposure to moving or complex visual stimuli, such as a scrolling feed. The criteria also note that PPPD may be precipitated by conditions that disrupt balance or cause vertigo, unsteadiness or dizziness, and that it may be present alone or alongside other conditions. Screen dizziness that persists can therefore be a sign that something else started it, and finding that earlier event is part of the evaluation.
What people most often misunderstand is the aim of rehabilitation. The goal is a balance system that leans less on vision, which is a different thing from avoiding screens. A 2013 review by Bronstein, Golding and Gresty describes the core therapy for visual vertigo as progressive desensitization: graded, repeated exposure to the visual motion that provokes symptoms, with explanation and reassurance.
In studies of people with vestibular dysfunction, visual vertigo symptoms can improve when customized vestibular rehabilitation exercises are combined with graded exposure to moving visual stimuli (Pavlou, Journal of Neurologic Physical Therapy, 2010). For one specific balance problem, vestibular hypofunction, meaning an inner ear that responds weakly on one or both sides, a clinical practice guideline from the Academy of Neurologic Physical Therapy states that clinicians should offer vestibular rehabilitation to adults with unilateral and bilateral vestibular hypofunction. Whether any of this applies to you depends on what the evaluation finds. Rehabilitation may be part of a plan when clinically appropriate, it does not help everyone, and I would rather tell you that before you start than after.
Common Questions About Dizziness When Scrolling
Can too much screen time cause vertigo?
Screens can provoke dizziness when scrolling, and sometimes true spinning vertigo, in a balance system that is already sensitive. Large areas of complex movement can make long-lasting dizziness worse, and a feed is exactly that. Spinning vertigo from a screen is a reason to have the inner ear and any migraine history examined rather than to blame the phone.
How long does digital vertigo last?
There is no fixed number, and I distrust pages that give one. A motion-sickness type episode usually settles once the mismatch stops and the eyes rest on something still. Dizziness that is present on most days for months, and worse upright or in visually busy places, is the pattern of persistent postural-perceptual dizziness and deserves an evaluation.
Is digital vertigo the same as visual vertigo?
Broadly, yes. Digital vertigo is the everyday name for the screen-triggered version; visual vertigo and visually induced dizziness are the clinical umbrella terms for dizziness or unsteadiness provoked by visual motion and complex patterns, whether from a screen, a supermarket aisle or moving traffic. Neither name is a diagnosis in itself.
Does the reduce-motion setting actually help?
It can help some people, since it reduces the parallax and animation effects that make a static screen behave like a moving one. Pair it with brightness matched to the room, the device held at eye level, and regular looks into the distance. If dizziness when scrolling continues after those changes, the settings were never the limiting factor.
Where can dizziness when scrolling be evaluated near Calabasas?
California Brain & Spine Center is at 4768 Park Granada, Ste 107, Calabasas, CA 91302, serving Calabasas, Encino and the greater Los Angeles area. Dr. Alireza Chizari, DC, DACNB performs the eye-movement, inner-ear and balance evaluation for dizziness when scrolling personally. Book a complimentary consultation at californiabrainspine.janeapp.com or call (818) 649-5300.
This content is for educational purposes only and is not medical advice. Consult a qualified healthcare provider about your specific situation.
If dizziness when scrolling is your problem, change the settings tonight and notice what happens over a week. If the sway shrinks, you have learned something useful and cheap. If it does not, or if it was never only the phone, the useful next step is to measure the balance system that is reacting rather than to keep removing the things it reacts to. California Brain & Spine Center | (818) 649-5300 | Calabasas, CA 91302, or book at californiabrainspine.janeapp.com.
Find Out What Your Balance System Is Reacting To
A 120-minute neurodiagnostic assessment with Dr. Alireza Chizari, DC, DACNB measures eye movements, inner-ear responses and the balance system before anyone recommends care. California Brain & Spine Center, 4768 Park Granada, Ste 107, Calabasas, CA 91302.

Dr. Alireza Chizari
This article has been medically reviewed for clinical accuracy by Dr. Alireza Chizari, DC, DACNB. Committed to evidence-based practice, Dr. Chizari ensures all content reflects the highest standards of functional neurology care.
Comments
Find our article more easily in Google.
FAQ
What is Functional Neurology?
Functional Neurology is a healthcare specialty that focuses on assessing and rehabilitating the nervous system’s function. It emphasizes neuroplasticity—the brain’s ability to adapt and reorganize—using non-invasive, evidence-based interventions to improve neurological performance.
How does Functional Neurology differ from traditional neurology?
Traditional neurology often concentrates on diagnosing and treating neurological diseases through medications or surgery. In contrast, Functional Neurology aims to optimize the nervous system’s function by identifying and addressing dysfunctions through personalized, non-pharmaceutical interventions.
Is Functional Neurology a replacement for traditional medical care?
No. Functional Neurology is intended to complement, not replace, traditional medical care. Practitioners often collaborate with medical professionals to provide comprehensive care.
What conditions can Functional Neurology help manage?
Functional Neurology has been applied to various conditions, including:
• Concussions and Post-Concussion Syndrome
• Traumatic Brain Injuries (TBI)
• Vestibular Disorders
• Migraines and Headaches
• Neurodevelopmental Disorders (e.g., ADHD, Autism)
• Movement Disorders
• Dysautonomia
• Peripheral Neuropathy
• Functional Neurological Disorder (FND)
Can Functional Neurology assist with neurodegenerative diseases?
While Functional Neurology does not cure neurodegenerative diseases, it can help manage symptoms and improve quality of life by optimizing the function of existing neural pathways.
What diagnostic methods are used in Functional Neurology?
Functional Neurologists employ various assessments, including:
• Videonystagmography (VNG)
• Computerized Posturography
• Oculomotor Testing
• Vestibular Function Tests
• Neurocognitive Evaluations
How is a patient’s progress monitored?
Progress is tracked through repeated assessments, patient-reported outcomes, and objective measures such as balance tests, eye movement tracking, and cognitive performance evaluations.
What therapies are commonly used in Functional Neurology?
Interventions may include:
- Vestibular Rehabilitation
- Oculomotor Exercises
- Sensorimotor Integration
- Cognitive Training
- Balance and Coordination Exercises
- Nutritional Counseling
- Lifestyle Modifications
Are these therapies personalized?
Absolutely. Treatment plans are tailored to the individual’s specific neurological findings, symptoms, and functional goals.
Who can benefit from Functional Neurology?
Individuals with unresolved neurological symptoms, those seeking non-pharmaceutical interventions, or patients aiming to optimize brain function can benefit from Functional Neurology.
Is Functional Neurology suitable for children?
Yes. Children with developmental delays, learning difficulties, or neurodevelopmental disorders may benefit from Functional Neurology approaches.
How does Functional Neurology complement other medical treatments?
It can serve as an adjunct to traditional medical care, enhancing outcomes by addressing functional aspects of the nervous system that may not be targeted by conventional treatments.
How is technology integrated into Functional Neurology?
Technological tools such as virtual reality, neurofeedback, and advanced diagnostic equipment are increasingly used to assess and enhance neurological function.
What is the role of research in Functional Neurology?
Ongoing research continues to refine assessment techniques, therapeutic interventions, and our understanding of neuroplasticity, contributing to the evolution of Functional Neurology practices.