What the evidence says about treating vestibular neuritis, why some people stay dizzy for months, and when sudden vertigo needs an emergency room first.
Vestibular neuritis treatment usually has two parts. The first is getting through the rough early days safely. The second is helping your brain adapt to a balance nerve that has been knocked off line. Research suggests that the second part shapes how you feel months later, and it is where vestibular rehabilitation comes in.
I am Dr. Alireza Chizari, DC, DACNB, a Board-Certified Functional Neurologist in Calabasas, and I wrote this for both moments. The first is the day the room starts spinning. The second comes weeks later, when you are back at work and getting through meetings on a fraction of your usual focus, still not quite steady.
If you are in that second stage, a dizziness evaluation in Calabasas looks at how your balance system is adapting, which is the question a diagnosis of vestibular neuritis leaves open. Below is what the evidence supports, how long recovery tends to take, and the one situation where you need an emergency room instead.
Key Takeaway
Vestibular neuritis is inflammation of the balance nerve in the inner ear, usually after a viral infection. Vestibular rehabilitation is supported by a Cochrane review as safe and effective, and guidelines favor starting it early. Long-term suppressant medicines may slow recovery. Lingering dizziness is associated with how the brain adapts. Sudden severe vertigo needs emergency care first.
What Does Vestibular Neuritis Treatment Involve?
Usually, vestibular neuritis treatment means getting through the acute days with medical care, then starting vestibular rehabilitation, an exercise-based therapy that a Cochrane review found safe and effective for one-sided inner-ear balance loss. A clinical practice guideline from the APTA Academy of Neurologic Physical Therapy recommends offering it and supports starting within the first two weeks.
Medicines in the First Days
Medicines are a short-term tool in vestibular neuritis. Vestibular suppressant medicines are sometimes used to blunt the spinning in the first days. Clinical guidance from NHS Dumfries and Galloway notes that these drugs may prevent central compensation, the brain's adaptation to a weakened balance nerve, and prolong symptoms, so it favors withdrawing them gradually where possible. That decision belongs to the clinician who prescribed them.
Corticosteroids are the other medicine people ask about. A Cochrane review of corticosteroids for vestibular neuritis found that an early effect on caloric test results (a measure of how the inner ear responds) did not last, and that symptomatic recovery did not differ from placebo. The authors concluded that there is insufficient evidence to support giving them.
Vestibular Rehabilitation and Gaze Stabilization
Vestibular rehabilitation is an exercise-based therapy that helps the brain work with the balance signals it now receives. A Cochrane review of vestibular rehabilitation concluded that it is a safe, effective management for unilateral peripheral vestibular dysfunction, the category that includes vestibular neuritis.
The updated clinical practice guideline on vestibular rehabilitation recommends that clinicians offer it to people with acute or subacute one-sided vestibular hypofunction, meaning weakened balance-nerve function on one side that began in the last few days (acute) or the past several weeks (subacute), and it cites newer evidence for starting within the first two weeks of onset. It describes clinic visits paired with a home exercise program.
That home program usually centers on gaze stabilization exercises, which ask your eyes to stay fixed on a target while your head moves, and the guideline treats them as a core part of care. Which ones you do, and how fast they progress, depends on what an evaluation finds.
What Is Vestibular Neuritis, and How Is It Different From Labyrinthitis?
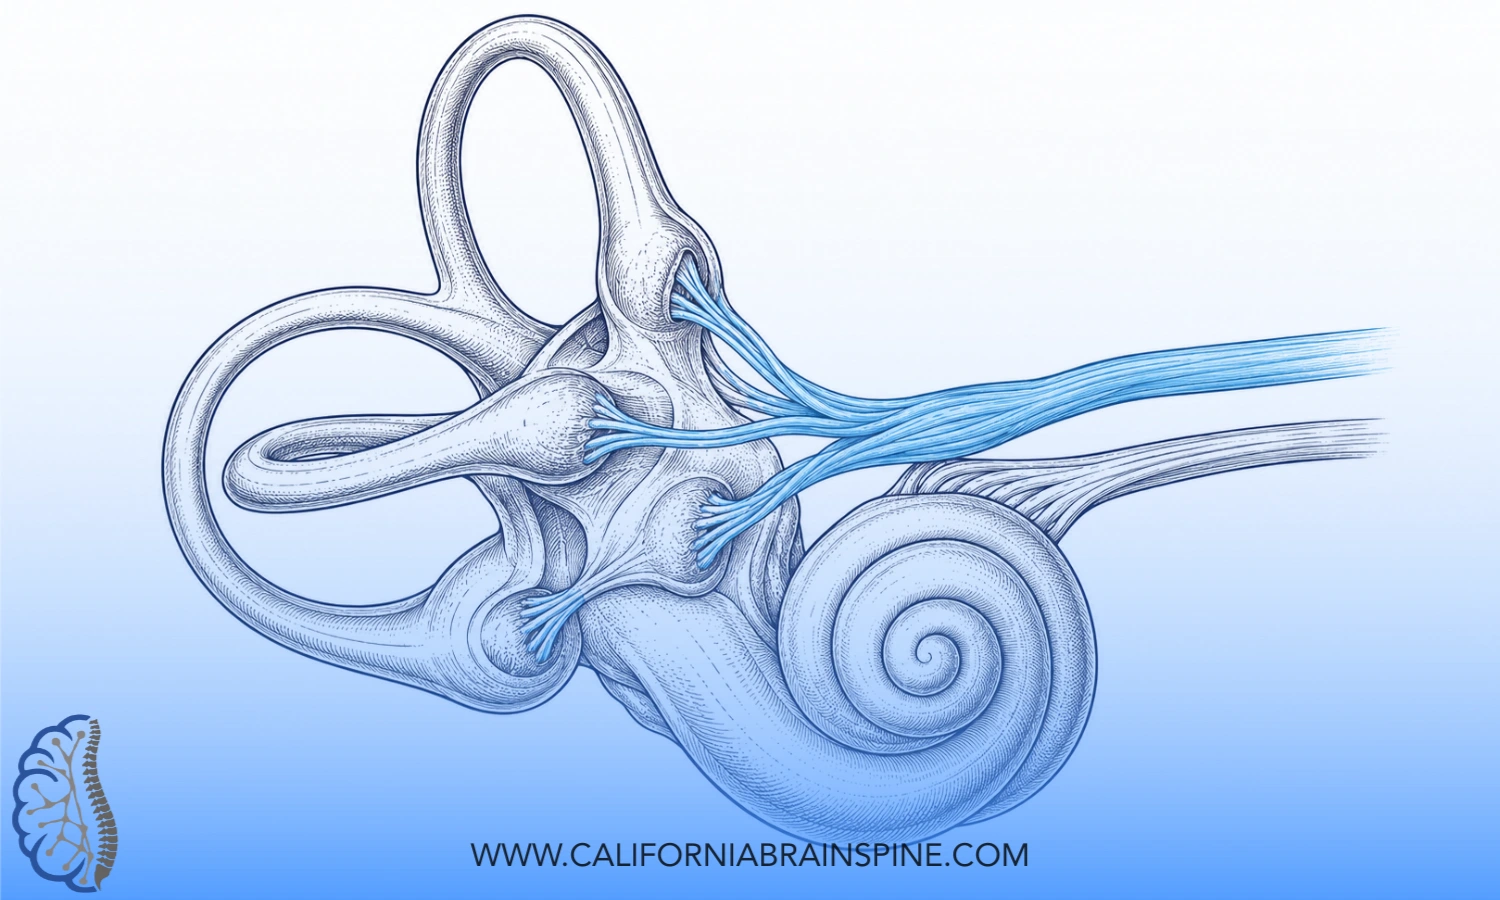
Vestibular neuritis is inflammation or swelling of the vestibular nerve, the inner-ear nerve that carries balance information to your brain, as Cleveland Clinic describes it. The NHS says it is usually caused by a viral infection, such as a cold or flu.
Vestibular neuritis symptoms typically arrive as a sudden attack of constant vertigo, with nausea and unsteadiness. Its sibling diagnosis, labyrinthitis, looks much the same. The usual way to tell them apart is hearing: according to the NHS, vestibular neuritis does not cause hearing loss or tinnitus, so a change in hearing points toward labyrinthitis instead.
How Long Does Vestibular Neuritis Last?
How long vestibular neuritis lasts depends on the person, and the honest answer comes in two halves. The NHS says many people get their balance back over 2 to 6 weeks, although it can take longer.
For a sizeable group it takes much longer. NHS clinical guidance on vestibular rehabilitation notes that symptoms persisting from months to years have been reported in 30 to 50 percent of cases of peripheral vestibular disorders, the group vestibular neuritis belongs to. A slow vestibular neuritis recovery time is common enough that it says nothing about you having done something wrong.
A practical threshold helps here. If dizziness lasts more than a few weeks, keeps getting worse, or comes with new symptoms, it is worth an evaluation.
Still not steady weeks after vestibular neuritis?
A detailed evaluation of how your balance system is adapting can help clarify what is keeping the dizziness going. It starts with a complimentary consultation at our Calabasas office.
Why Am I Still Dizzy Months After Vestibular Neuritis?
Lingering dizziness after vestibular neuritis appears to depend less on how much inner-ear damage remains than on how the brain adapts to it. That is the conclusion of a review of long-term outcome in vestibular neuritis by Bronstein and Dieterich.
What Central Compensation Means
When one balance nerve is weakened, your brain receives uneven signals from the two sides and has to adapt to them. Clinicians call that adaptation central compensation. When it is incomplete, dizziness can continue after the acute illness has passed, which is why the same diagnosis can mean a few weeks of trouble for one person and months for another.
Visual Dependence and Anxiety Traits
The same review found that visual dependence, anxiety and somatization traits (a tendency to feel stress as physical symptoms) predict the development of chronic dizziness. Visual dependence means leaning heavily on your eyes to judge where you are in space.
None of this means the dizziness is imagined
In that review, visual dependence and anxiety traits are factors that predict who goes on to develop chronic dizziness after vestibular neuritis, a real injury to the balance nerve. They are things an evaluation can look at and a rehabilitation plan may address, and naming them is a step toward help.
How Do the Treatment Options for Vestibular Neuritis Compare?
The treatment options for vestibular neuritis rest on very different levels of evidence, and the table below sets them side by side.
| Option | What it is aimed at | What the evidence says |
|---|---|---|
| Vestibular suppressant medicines | Easing the spinning sensation | NHS guidance says they may prevent central compensation and prolong symptoms; gradual withdrawal is favored where possible, decided by the prescriber |
| Corticosteroids | Reducing nerve inflammation | Cochrane review: insufficient evidence to support them; no difference from placebo in symptomatic recovery |
| Vestibular rehabilitation | Helping the brain adapt to uneven balance signals | Cochrane review: a safe, effective management for one-sided peripheral vestibular loss |
| Gaze stabilization home exercises | Keeping vision steady while the head moves | Clinical practice guideline: a core part of rehabilitation, paired with clinic visits |
| Starting rehabilitation early | Beginning adaptation sooner | Clinical practice guideline cites newer evidence for starting within the first two weeks |
| Evaluation for lingering dizziness | Finding what keeps symptoms going | Bronstein and Dieterich review: chronic dizziness is associated with visual dependence and anxiety traits |
When Is Sudden Vertigo an Emergency?
Sudden, constant vertigo should be treated as an emergency until a medical clinician has ruled out a stroke. A systematic review on acute vestibular syndrome explains that this kind of attack can come from a stroke in the back of the brain rather than the inner ear, and that telling the two apart can be challenging.
When to seek emergency care
If symptoms come on suddenly or severely - a sudden severe headache, weakness, trouble speaking, vision loss, or fainting - that is an emergency. Call 911 or go to an emergency room, not a clinic appointment.
A first attack of severe, constant vertigo deserves urgent medical assessment before anyone settles on vestibular neuritis as the explanation.
Vestibular Neuritis Treatment in Calabasas
Vestibular neuritis treatment at California Brain & Spine Center is aimed at the stage after the emergency, when the room has stopped spinning but you are still not steady. Dr. Alireza Chizari, DC, DACNB, a Board-Certified Functional Neurologist at California Brain & Spine Center in Calabasas, works with people from across the 101 corridor, including Woodland Hills.
Care may include vestibular rehabilitation when clinically appropriate after evaluation. The practice works alongside primary care, ENT and medical neurology, and any question about a medicine goes back to the clinician who prescribed it.
When the main problem has become unsteady walking or a fear of falling, balance disorder therapy may be part of the plan.
What Happens at a First Visit for Lingering Dizziness?
A first visit for lingering dizziness after vestibular neuritis starts with a 120-minute neurodiagnostic assessment of how your eyes, inner ears and balance work together. One question patients often ask me is why they are still dizzy when they were told the inflammation had passed. I cannot answer that from the diagnosis alone, which is why I test before I suggest anything.
In practice that means looking at your eye movements, your balance under different conditions, and the vestibulo-ocular reflex, the reflex that keeps your vision steady when your head moves. Another question I hear is whether the exercises someone printed off the internet are the right ones. Sometimes they are, and the test results are what tell me which ones to keep, which to change, and how quickly to progress them. I go through each result in plain language, so you leave knowing what was measured and why it matters for the plan.
"Then we did the full examinations like eye tracking and balance test and he explained my results and what they mean for my symptoms."
From a Google review

What Else Do People Ask About Vestibular Neuritis?
Vestibular neuritis raises a handful of practical questions beyond treatment itself, and these are the ones that come up most often.
Does vestibular neuritis go away on its own?
For many people, yes. The NHS says balance usually returns over 2 to 6 weeks, though it can take longer, and persistent vestibular neuritis symptoms have been reported in 30 to 50 percent of peripheral vestibular cases. When dizziness lingers past a few weeks, an evaluation can help guide vestibular neuritis treatment from there.
Which vestibular neuritis exercises are usually prescribed?
Gaze stabilization exercises are a core part of vestibular neuritis treatment, according to the APTA clinical practice guideline, which pairs clinic visits with a home program. The right vestibular neuritis exercises depend on what your evaluation shows, so they are chosen and progressed for you instead of copied from a video.
Can meclizine be used for vestibular neuritis?
Whether meclizine suits you is a question for your prescriber. Vestibular suppressant medicines are sometimes used for the spinning, and NHS guidance notes they may prevent central compensation and prolong symptoms, so it favors gradual withdrawal where possible. Any change to a medicine is a decision for the clinician who prescribed it, never something to try alone.
Labyrinthitis vs vestibular neuritis: how can you tell them apart?
The labyrinthitis vs vestibular neuritis question usually comes down to hearing. Both can cause vertigo, unsteadiness and nausea, and both usually follow a viral infection such as a cold or flu. According to the NHS, vestibular neuritis does not cause hearing loss or tinnitus, so a change in hearing points toward labyrinthitis.
Where can I get vestibular neuritis treatment in Calabasas or Los Angeles?
California Brain & Spine Center in Calabasas offers evaluation for people still dizzy after vestibular neuritis, with vestibular rehabilitation when clinically appropriate. Vestibular neuritis treatment there starts with a complimentary consultation, then a 120-minute neurodiagnostic assessment. The practice serves the greater Los Angeles area along the 101. Call (818) 649-5300 to book.
The next step depends on where you are: a sudden first attack belongs in an emergency room, and dizziness that lingers for weeks after vestibular neuritis is worth an evaluation. I would rather you have it checked than wait for it to become your new normal. Vestibular neuritis treatment works on adaptation, and the research on vestibular rehabilitation suggests that adaptation can still be supported after the acute illness is over.
If you would like to talk it through, I am Dr. Alireza Chizari, DC, DACNB, and the first conversation is a complimentary consultation.
California Brain & Spine Center | (818) 649-5300 | Calabasas, CA 91302
Book online at californiabrainspine.janeapp.com
This content is for educational purposes only and is not medical advice. Consult a qualified healthcare provider about your specific situation.
Talk through your dizziness with Dr. Chizari
Bring your questions about vestibular neuritis, the exercises you have tried, and what the past weeks have been like. A complimentary consultation in Calabasas is the place to start.