

What breathwork calls carbon dioxide tolerance, what the physiology underneath it actually is, and when a breathing pattern belongs in a dizziness workup.
Here is the short answer. CO2 tolerance, or carbon dioxide tolerance, is a term from the breathwork world rather than a medical diagnosis, and the physiology underneath it is how sensitive your breathing drive is to that gas. When you breathe more than your body needs, blood carbon dioxide falls, and low carbon dioxide can narrow the small vessels that supply the brain. That is one of the routes from an ordinary breathing habit to a dizzy morning.
I practice functional neurology in Calabasas, and this question tends to arrive in a familiar shape. The scans came back normal. The blood work came back normal. Someone has already offered anxiety as the explanation. And the symptoms keep their own schedule anyway: the long phone call, the stairs out of the parking structure, the grocery aisle where the shelves seem to lean.
So this article stays with the mechanism, because the mechanism is the part you can actually use. What carbon dioxide does in the body, why a breathing pattern drifts, what low carbon dioxide does to blood flow in the brain, and how much of that is worth checking before anyone decides your breathing is the culprit. The honest version comes with limits, and there are several.
Key takeaway
Carbon dioxide tolerance is a breathwork term for how strongly your breathing responds to rising carbon dioxide. It is not a diagnosis. Breathing more than you need lowers blood carbon dioxide, which can narrow vessels in the brain and produce dizziness, air hunger and tingling. A breathing pattern is worth examining, after other causes of dizziness have been considered.
What is CO2 tolerance?
Carbon dioxide tolerance is a term used in breathwork circles for how well a person tolerates rising carbon dioxide before the urge to breathe takes over. The clinical ideas behind it are chemoreceptor sensitivity, how strongly the sensors that monitor carbon dioxide push you to breathe, and hypocapnia, the low blood carbon dioxide that follows over-breathing.
The phrase comes out of breath training, where it usually describes how long somebody can sit with the urge to breathe before that urge wins. In a clinic the same territory carries different names, and the names matter because they point at things that can be observed and reasoned about rather than scored.
Nobody has a carbon dioxide tolerance the way they have a blood type. What people have is a breathing pattern, a set of carbon dioxide sensors that has adapted to that pattern, and a set of symptoms that show up when the two are out of step with what the moment demands.
How carbon dioxide sets your breathing drive
Most people assume breathing is about oxygen. Oxygen is the purpose, but it is not the thermostat. The classical physiology, laid out in the respiratory control chapters of Guyton and Hall's textbook of medical physiology, is that carbon dioxide and the acidity it produces are the main signals telling the brainstem how often and how deeply to breathe. Oxygen takes the controls only when it drops a long way, which for most people is a rare event.
That arrangement works beautifully and it is also easy to override. If your default pattern runs slightly ahead of your metabolic need, carbon dioxide drifts down and stays down. A person can talk through an entire meeting without once noticing they are doing it. The system adjusts to the new level. Then the level that used to be normal starts to register as too much, which is the part that catches people out.
Why tolerance is a breathwork word rather than a clinical one
Search the phrase and you will meet timed breath holds, usually taken after a relaxed exhale and read back as a grade for your breathing. Breath-hold time moves with lung volume, with effort, with motivation, with distraction and with practice, which makes it a training metric rather than a clinical measurement. Nothing inside that number separates a breathing pattern from an inner ear problem, a blood pressure problem or a medication effect.
I have no quarrel with breath training as training. My quarrel is with reading a score as a diagnosis, because the score can look poor in somebody whose dizziness has nothing to do with breathing, and it can look respectable in somebody whose dizziness clearly does. A number that cannot tell those two people apart should not be deciding what either of them does next.
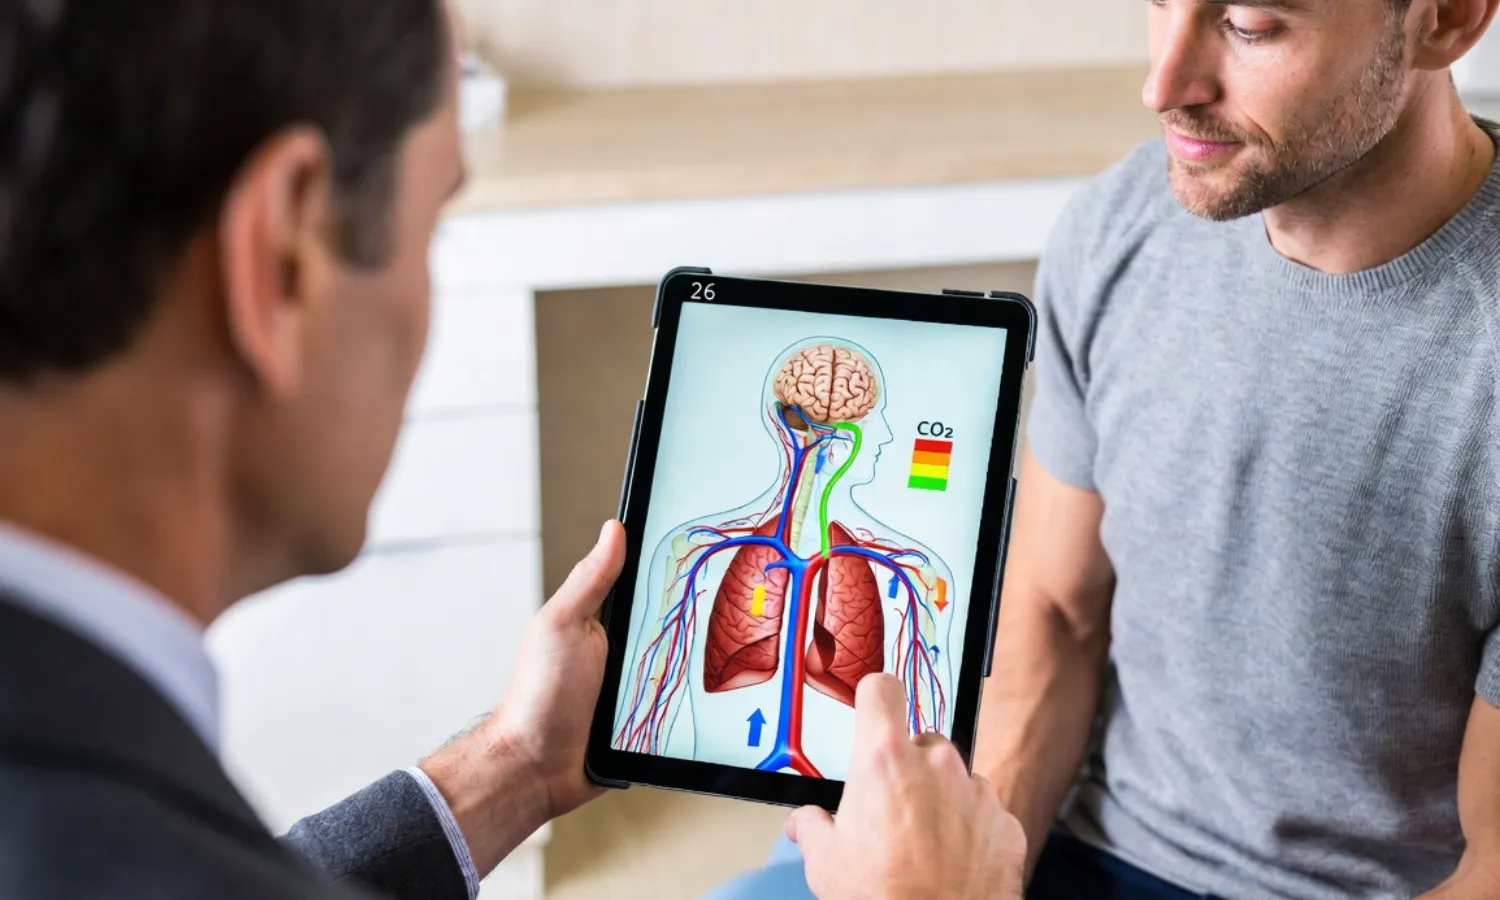
What are the symptoms of low carbon dioxide?
Low carbon dioxide symptoms usually include lightheadedness, a feeling of not getting a satisfying breath, tingling in the fingers or around the mouth, chest tightness, and a sense of being slightly detached from the room. These sensations have a physiological basis, and they remain real when anxiety is part of the picture.
Hyperventilation syndrome is the clinical label for the version of this that reaches an examination room, and the symptom description published by Cleveland Clinic is consistent with what patients report: dizziness, breathlessness in the presence of perfectly adequate breaths, tingling, chest tightness, and often a wave of fear that arrives alongside the physical sensations rather than before them.
The detail that persuades most people something is wrong is the breath that never finishes. You take one in, it does not land, so you take a bigger one, and the bigger one does not land either. From the inside this reads as a shortage of air. From the physiology side, the more likely story is a carbon dioxide level that is already low and a brainstem that has learned to treat any rise in it as an alarm. Breathlessness that does not match the effort you are making deserves attention in its own right.
Timing tells you more than intensity does. These symptoms tend to cluster around specific situations rather than spreading evenly across the day, and the situations repeat.
- Long stretches of talking, because speech puts breathing on the rhythm of the sentence rather than the rhythm of the body, which is why a busy phone day can end in lightheadedness
- Stairs, hills and the first minutes of exercise, when breathing frequently overshoots the actual demand before it settles into it
- Arguments, deadlines and anything with adrenaline in it, which lift breathing rate before they lift anything you would notice
- Crowded, bright or visually busy places, where the visual and balance systems are already working harder and have less tolerance for a drop in blood flow
Why does over-breathing make you dizzy?
Low arterial carbon dioxide narrows the arteries of the brain and can reduce cerebral blood flow. The effect is one of the better described relationships in respiratory physiology, reviewed in detail in the New England Journal of Medicine review of hypocapnia by Laffey and Kavanagh, and it is the reason a breathing change can produce a neurological symptom without anything being wrong with the brain itself.
A brain running on slightly less flow than it expects does not switch off. It complains. The complaint sounds like lightheadedness, a lag when you turn your head quickly, blurring at the edges of vision, a floor that feels half a second behind your feet. None of that requires a lesion. It requires a supply line that has tightened for a chemical reason, and it can settle again when the chemistry does.
Air hunger is the symptom that convinces people they are short of oxygen, when the trouble may sit on the other side of the equation.
There is a loop in this, which is what makes it stubborn. The dizziness is unpleasant, unpleasant sensations raise breathing, raised breathing lowers carbon dioxide further, and the dizziness gets a second wind. People then do the thing everybody recommends, which is to take a big deep breath, and it can make the next few minutes worse. That single piece of advice causes a good deal of confusion.
Tingling belongs to the same pattern. Hyperventilation syndrome is associated with tingling in the hands or around the mouth, and fingers, toes and the skin around the mouth tend to report it first. It is a reliable companion of the pattern and it frightens people badly, particularly when it arrives on a freeway.
Is this carbon dioxide tolerance, or is it anxiety?
Usually both are in the room, and the order they arrived in matters less than people expect. Anxiety drives breathing, quickly and efficiently. Breathing that has drifted produces sensations with the physical signature of anxiety, including a fast heart, tight chest, tingling hands and a conviction that something serious is about to happen. Either one can start the cycle. Once the cycle is running, the starting point is mostly of historical interest.
Being told that a symptom involves anxiety and being told that nothing is happening are two different statements, and they often get delivered as if they were the same one. The second is what people carry home. It is also the reason a patient will sit in my office and describe the tingling in their hands with an apology attached, as though describing it accurately were a form of exaggeration.
The practical value of the breathing explanation is that it gives you something observable. A thought is hard to examine in a clinic. A breathing pattern can be watched at rest, watched while somebody stands up, watched while they read a paragraph out loud, and watched while they do a task that loads their attention. That is why it belongs in an evaluation rather than in a reassurance.

Not sure whether your breathing belongs in this picture?
A functional neurology assessment in Calabasas examines breathing alongside eye movements, balance and autonomic responses, so the question gets answered in context rather than in isolation.
How would you notice a breathing pattern in yourself?
Dysfunctional breathing is the research term for the territory, described in a review in the Jornal Brasileiro de Pneumologia as a respiratory condition characterized by irregular breathing patterns that occur either in the absence of concurrent diseases or secondary to cardiopulmonary diseases. The second half of that sentence is the important half. A breathing pattern can sit on its own, and it can also sit on top of a heart or lung problem that needs its own attention first.
The features clinicians look for are unglamorous. Movement that starts at the top of the chest before the lower ribs and belly join in. Frequent sighing. Yawning that has nothing to do with sleep. Habitual mouth breathing at rest. Small breath holds in the middle of a sentence or while concentrating. During a history I am listening to what a person says and also counting their sighs, and patients are almost always surprised when I mention it, because sighing is invisible from the inside.
You can observe the same things at home, with one condition attached: this is noticing, not diagnosing. Bring what you notice to an appointment rather than acting on it.
- Set a quiet moment and see whether your breath enters through the nose or the mouth, and whether the top of your chest moves before your lower ribs do
- Count sighs across an afternoon rather than a minute, since the pattern shows up over hours and disappears when you watch for it
- Notice what your breathing does in the first sentence of a difficult conversation, because that is usually where the change starts
- Track which situations the dizziness follows, given that a symptom tied to talking, stairs and stress behaves differently from one tied to head position
That last distinction is the one worth carrying into an appointment, because it separates several very different problems that all feel like dizziness from the inside.
| Typical presentation | Patterns that suggest something more | What the evaluation looks at |
|---|---|---|
| Lightheadedness that builds during long talking, stairs or stress | Lightheadedness with chest pain, or fainting that arrives without warning | Cardiovascular review before any breathing work, with blood pressure and heart rate measured in different positions |
| Tingling in the fingers or around the mouth during episodes | Numbness that stays on one side of the body, or persists between episodes | Neurological examination, with referral to medical neurology when the pattern is one-sided |
| A room that seems to lag when you turn your head | True spinning triggered by one specific head position, reliably, every time | Positional testing for BPPV, the loose-crystal inner-ear problem, and assessment of the vestibular (inner-ear balance) system |
| Frequent sighing and a breath that never feels complete | Breathlessness present at rest, or worsening enough to limit walking | Medical work-up of heart and lung causes before a breathing pattern is assumed |
| Symptoms that began after a concussion and never settled | New symptoms appearing long after the head injury, or steadily worsening | Post-concussion assessment covering eye movements, balance and autonomic responses |
| Dizziness that is worse standing and eases lying down | Fainting on standing, or a heart rate that stays high for as long as you are upright | Orthostatic testing, with heart rate and blood pressure measured lying and then standing, and evaluation for dysautonomia |

Where does CO2 tolerance fit with POTS and dysautonomia?
This is where the breathing question stops being a side issue. Research on postural tachycardia syndrome published in the Journal of the American Heart Association described a subgroup of patients in whom standing is accompanied by over-breathing, low carbon dioxide and reduced cerebral blood flow, which may contribute to the lightheadedness they get upright. It is a subgroup finding rather than a description of everyone with POTS, and it explains why breathing keeps appearing in these conversations.
The autonomic nervous system and the respiratory system share wiring and share a rhythm. If your automatic control systems are already struggling, as they can be after a concussion, after a viral illness or in dysautonomia, an unstable breathing pattern is one more load on a system with little margin left.
The same wiring reaches further than most patients expect. If that combination sounds like your week, our article on whether digestive issues can aggravate dizziness and brain fog follows the same thread from a different end.

What does an evaluation in Calabasas actually look at?
Dizziness is one symptom with a long list of possible sources. The vestibular system, the cardiovascular system, the neurological system, medications and breathing all appear on that list, and a review in American Family Physician sets out how wide that list is. A breathing explanation is something you arrive at after working through the alternatives, never something you start with because it is the most interesting one.
At California Brain & Spine Center in Calabasas, Dr. Alireza Chizari, DC, DACNB, approaches this as a functional neurology assessment rather than a single test, and the breathing observations sit inside it rather than replacing it. A neurodiagnostic assessment may include eye movement and gaze stability testing, balance measurement under different sensory conditions, examination of the neck and its contribution to position sense, cognitive tasks that reliably provoke symptoms, and observation of breathing at rest, standing and during light effort. What is included depends on the presentation, and on what is clinically appropriate after the evaluation.
What a breathing questionnaire can and cannot do
The Nijmegen Questionnaire is a symptom checklist covering dizziness, tingling and breathlessness, and it is used as a screening aid for hyperventilation-related complaints. It is a way of organising a conversation and tracking whether symptoms shift over time. It is not a stand-alone diagnostic test, and a high score on it is a reason to examine somebody carefully rather than a finding in its own right.
The other half of the evaluation is scope. A functional neurology assessment is not imaging interpretation and it is not medication management. Where a finding points toward medical neurology, cardiology, ENT or a primary care work-up, that is where it goes, and the practice works alongside those clinicians rather than around them. Patients who have spent years being handed between offices tend to find that boundary reassuring rather than disappointing.
When this is not a breathing question at all
If symptoms come on suddenly or severely - a sudden severe headache, weakness, trouble speaking, vision loss, or fainting - that is an emergency. Call 911 or go to an emergency room, not a clinic appointment.
The same applies to chest pain, to breathlessness that arrives at rest and keeps building, and to a first seizure. Recurring dizziness that has been part of your life for months is a different problem from a symptom that arrives in minutes, and only one of the two belongs in an appointment diary.
Can breathing retraining help?
Honestly, the evidence here is thinner than the internet suggests. A Cochrane review of breathing exercises for dysfunctional breathing and hyperventilation syndrome in adults, published in the Cochrane Database of Systematic Reviews, found the controlled-trial base too limited to draw firm conclusions about benefit. Breathing retraining is used in practice, it may help some patients, and the research has not yet caught up with the enthusiasm around it. The data does not support promising more than that.
What retraining aims at is modest and specific: a quieter baseline pattern during ordinary activity, more nasal breathing at rest, less dominance from the upper chest, fewer unnecessary sighs and breath holds. It is not a breathing exercise performed once a day while the other waking hours run unchanged. The hours are the point.
There is a trap in it as well, which I mention to everyone. Watching your own breathing all day tends to make breathing worse, because attention alone changes the pattern. Short practices that fit inside a normal day may be easier to sustain than long sessions, and easier than vigilance.
- When dizziness starts, resist the big deep breath, since forcing volume usually drops carbon dioxide further and extends the episode
- Use brief resets rather than long sessions, because a minute of quiet nasal breathing between tasks is easier to sustain than a daily ritual
- Treat frequent sighing as information rather than a habit to suppress, given that it often marks the situations where the pattern destabilises
- Build activity gradually and in a way you can repeat, as movement is where breathing, circulation and balance may be trained together
For people whose dizziness has an inner-ear, vestibular component, breathing work sits beside vestibular rehabilitation rather than instead of it. The nervous system is being asked to learn that head movement, visual complexity and a shifting carbon dioxide level can all happen at once without danger, and that lesson may be easier to teach when the pieces are trained together.
Working with patients in Calabasas and Woodland Hills
Most of the people who bring me this question live within a short drive: Calabasas, Woodland Hills and the surrounding stretch of the San Fernando Valley and the 101 corridor. A number of them have already been through vestibular therapy, through cardiology, and through a round of imaging that found nothing, which is often when the breathing question comes up.
The practice is a functional neurology clinic rather than a breathing clinic, and that distinction is deliberate. Breathing is examined because it interacts with balance, blood flow and autonomic control, not because it is assumed to be the answer. You can read more about how the assessment is structured at californiabrainspine.com.

Questions patients ask about CO2 tolerance and dizziness
Can a breathing pattern by itself make you dizzy?
It can. Breathing more than your body needs lowers blood carbon dioxide, and low carbon dioxide can narrow vessels in the brain and reduce flow. In some people that is enough to produce lightheadedness, which is the link behind the CO2 tolerance question. In many others it sits on top of a vestibular or autonomic problem and makes it louder.
Is there a CO2 tolerance test worth doing at home?
Not as a diagnostic. The breath-hold scores sold as CO2 tolerance tests move with lung volume, effort, practice and mood, and none of them separate a breathing pattern from an inner ear or blood pressure cause. Watching how you breathe during an ordinary day tells a clinician more than a timed number does.
Why do I feel short of breath when my oxygen reading is normal?
The breathing drive answers mainly to carbon dioxide rather than to oxygen, so air hunger can arrive while oxygen is fine. Low carbon dioxide symptoms can include that exact sensation, a breath that never feels finished, while a pulse oximeter reads fine. The reading is answering a different question from the one your body is asking.
Does a breathing explanation mean my dizziness is anxiety?
No. Anxiety can drive over-breathing, and over-breathing can manufacture sensations that feel like anxiety, so the two travel together often. Naming a breathing pattern describes a mechanism, and it says nothing about whether you imagined your symptoms. The physiology runs the same way in a calm person and a frightened one.
Do I need to be in Calabasas to have this evaluated?
An in-person assessment is the practical starting point, and patients reach the Calabasas office from Woodland Hills and across the San Fernando Valley. CO2 tolerance questions are examined alongside eye movements, balance and autonomic responses, and that combination is difficult to judge at a distance or from a questionnaire alone.
If your dizziness changes with talking, with stairs, with stress or with a crowded room, your breathing is worth putting on the list. Not at the top of it, and not instead of the cardiac, vestibular and neurological questions, but on it. Carbon dioxide tolerance is a rough name for a real piece of physiology, and the physiology is checkable even when the name is not clinical.
What I would avoid is the shortcut in either direction: deciding your breathing explains everything, or deciding it explains nothing because a scan was clean. Both skip the evaluation, and the evaluation is what tells you which one you are dealing with. If you want that conversation, you can reach us at California Brain & Spine Center | (818) 649-5300 | Calabasas, CA 91302, or book a complimentary consultation online.
This content is for educational purposes only and is not medical advice. Consult a qualified healthcare provider about your specific situation.
Bring the pattern you have already noticed
The situations that set your dizziness off are useful clinical information, and they are a reasonable place to start. Calabasas office, in person, with the breathing question examined in context.






